Section 1: Product Introduction & Clinical Purpose
The Curedent B Splint is a precision-milled, dual-arch diagnostic appliance engineered to verify complete condylar seating, diagnose vertical dimension of occlusion (VDO) collapse, and test orthopedic joint stability prior to definitive restorative treatment. Developed for general dentists, prosthodontists, TMD clinicians, and gnathology-focused practitioners, this Dawson-style Dawson B-Splint system provides a controlled interocclusal environment that allows the clinician to confirm true musculoskeletal joint position without interference from habitual closure patterns.
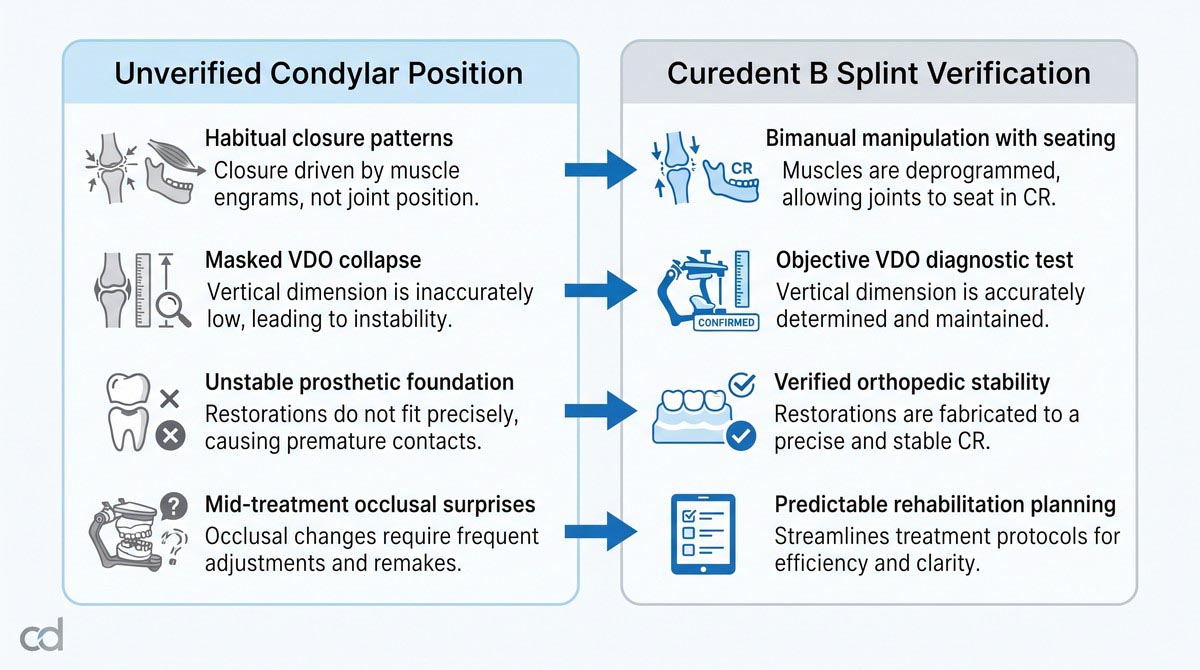
Full-mouth rehabilitation, implant-supported full-arch reconstruction, and complex occlusal therapy all depend on a single clinical prerequisite: the condyles must be verifiably seated in their true musculoskeletal position before occlusal records are captured and prosthetic designs are finalized. When the condyles are not completely seated—whether due to muscle bracing, habitual engram interference, or undiagnosed VDO collapse—every subsequent treatment decision carries increased risk of prosthetic misfit, occlusal instability, and long-term failure. The Curedent B Splint addresses this diagnostic challenge directly. By providing a dual-arch interocclusal platform, it allows the clinician to perform bimanual joint manipulation with the appliance seated, verify complete condylar seating, and confirm the true vertical dimension before committing to definitive treatment.
Key Clinical Advantages
- Verified Condylar Seating: Dual-arch interocclusal platform enables bimanual manipulation with the appliance seated for reliable joint position verification.
- Objective VDO Diagnostic: Provides a controlled platform to test for vertical dimension collapse without the confounding influence of habitual closure patterns.
- Orthopedic Joint Load Testing: Allows the clinician to apply controlled joint load and assess the patient’s orthopedic response before committing to definitive therapy.
- Dual-Arch Stability: Both maxillary and mandibular components are precision-milled to interlock, ensuring repeatable seating and reproducible diagnostic records.
- Integrated Digital Workflow: CAD-designed from intraoral scans and occlusal records for accurate adaptation and predictable clinical behavior.
Section 2: Product Anatomy & Physical Construction
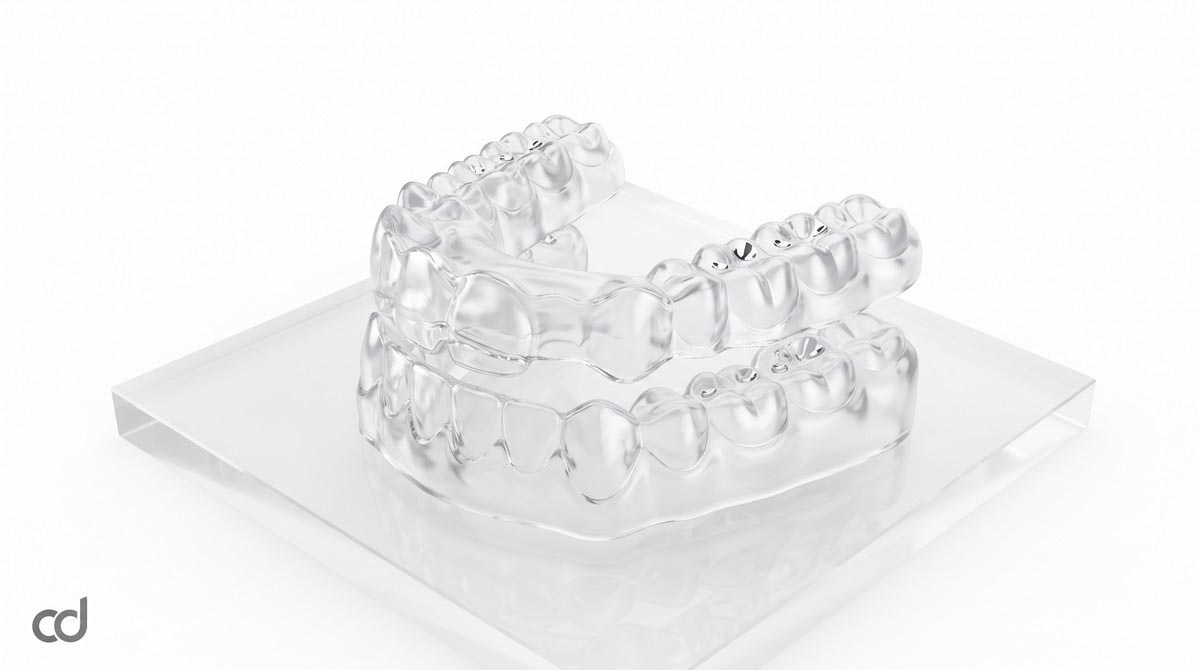
Medical-Grade Milled PMMA Construction
Both components of the Curedent B Splint are milled from high-density, medical-grade PMMA blanks or certified Class IIa biocompatible resin, depending on the clinical indication. The material provides high flexural strength, dimensional stability, and biocompatibility under diagnostic-phase intraoral wear. Unlike hand-fabricated cold-cure acrylic B-Splints that exhibit polymerization shrinkage and irregular interocclusal contacts, milled PMMA is fully pre-polymerized, ensuring uniform density and precise geometric execution across both arches.
The Dual-Arch Diagnostic System: Structural Foundation
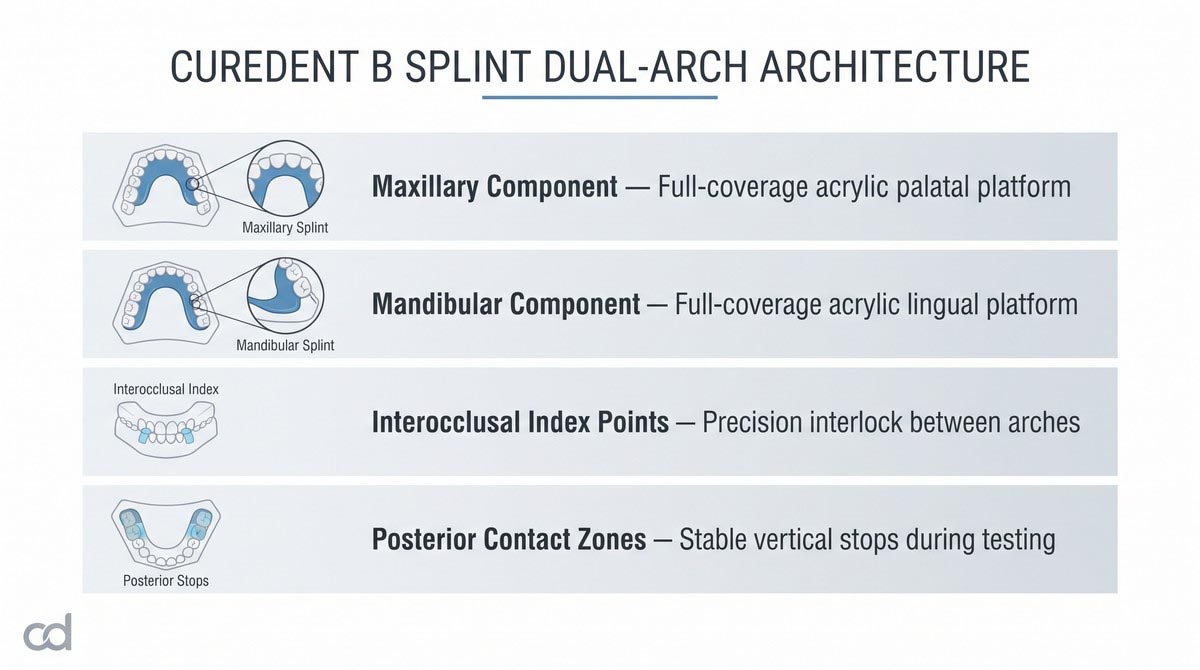
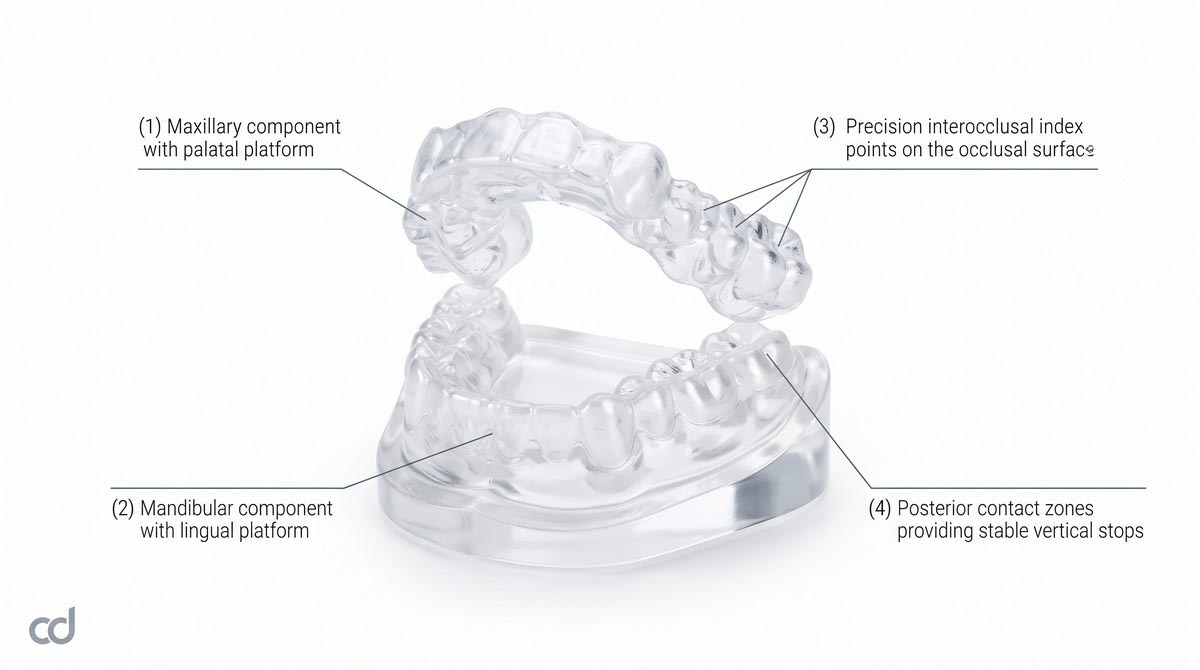
The defining feature of the dual-arch diagnostic system is its two-component architecture. Unlike a single-arch stabilization splint that seats only on the maxillary or mandibular arch, the B Splint includes both maxillary and mandibular components that interlock through precision-milled index points. This dual-arch design provides two critical advantages:
- Bilateral Support: Both arches are stabilized during diagnostic testing, preventing deflection or displacement under bimanual manipulation forces.
- Reproducible Interocclusal Relationship: The interlocking index points ensure that the two arches seat in a repeatable, verifiable position, allowing the clinician to capture consistent diagnostic records across multiple appointments.
The Maxillary Component: Palatal Platform
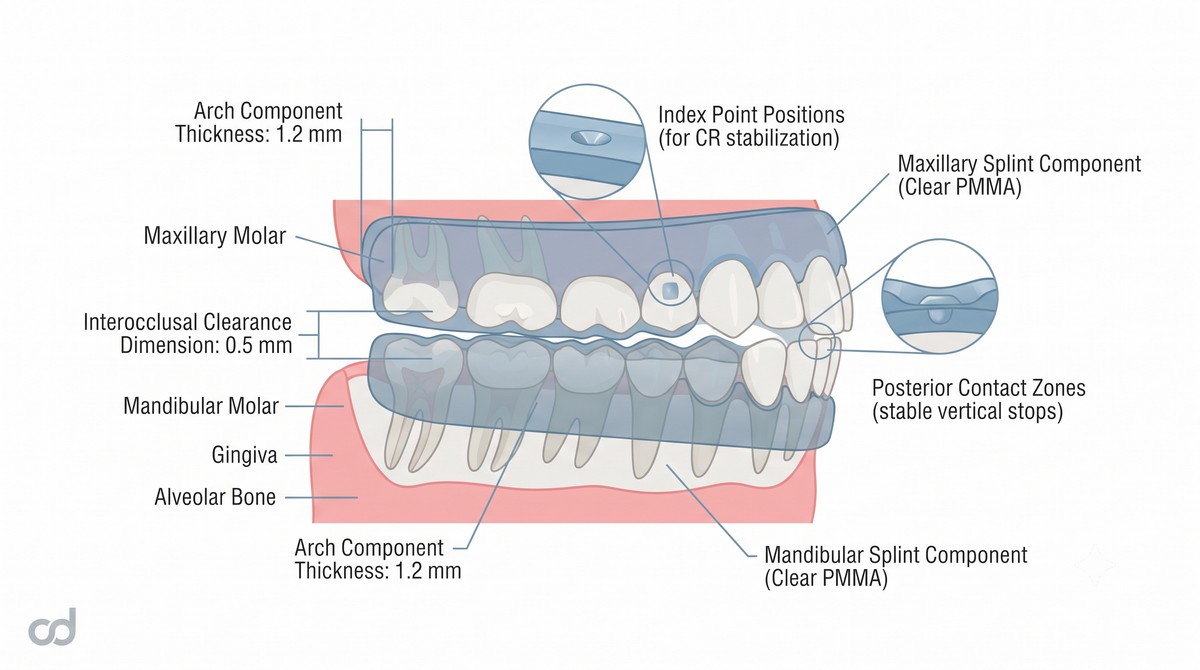
The maxillary component is milled as a full-coverage palatal platform that seats over the maxillary dentition. The intaglio surface is polished to eliminate pressure spots and ensure passive seating across the full arch. The occlusal surface incorporates the interocclusal index points and posterior contact zones that engage the mandibular component during diagnostic testing.
The Mandibular Component: Lingual Platform
The mandibular component mirrors the maxillary design, milled as a full-coverage lingual platform that seats over the mandibular dentition. The occlusal surface engages the maxillary component through the interlocking index points, creating a stable dual-arch diagnostic platform for bimanual manipulation and joint load testing.
Interocclusal Index Points and Contact Zones
The interlocking mechanism between the two arches is defined by precision-milled index points that register the two components in a reproducible interocclusal relationship. The posterior contact zones provide stable vertical stops that maintain the planned VDO during diagnostic testing. Both features are milled to tight tolerances—typically below 0.05 mm—to ensure that diagnostic records captured with the appliance in place are reproducible and clinically reliable.
Surface Finish and Marginal Adaptation
Both components are milled to uniform thickness that balances structural rigidity against interocclusal space requirements. Margins are finished with a smooth, rounded contour that seats 0.5–1.0 mm coronal to the gingival crest, protecting soft tissue while allowing unobstructed oral hygiene. The intaglio surfaces of both components are polished to eliminate pressure spots and ensure passive seating across both arches.
Digital Workflow and Milling Precision
[Intraoral Optical Scan (STL/PLY)] ──┐
├─► [Digital CAD Design] ──► [5-Axis Milled PMMA Dual-Arch System]
[Occlusal Records / Mounted Models] ┘
The appliance is designed entirely in CAD from the patient’s optical intraoral scans, occlusal registration data, and—when indicated—mounted articulator models. The digital design is executed on a 5-axis milling unit, producing both components as monolithic structures with precise interocclusal index points and clean marginal contours. The dual-arch design allows the clinician to test orthopedic joint stability without removing the appliance, enabling direct bimanual manipulation with the components in place.
How the Two Arches Interlock and Why Both Are Needed
A single-arch splint provides only one occlusal reference plane—the clinician can verify mandibular position relative to the splint, but cannot test both arches independently. The dual-arch B Splint provides two simultaneous references. With both components seated, the clinician can perform bimanual manipulation and observe how the mandible seats relative to the maxillary component through the interlocking index points. This dual-arch interlock is essential for reliable joint load testing and for capturing diagnostic records that reflect true condylar seating rather than muscle-braced positioning.

Section 3: Indications & Clinical Applications
Primary Clinical Indications
The Curedent B Splint is indicated across a range of complex diagnostic and rehabilitation-planning scenarios:
- Verifying True Condylar Seating Before Full-Mouth Rehabilitation: Cases where reliable condylar position must be confirmed before occlusal records are captured and prosthetic designs are finalized.
- Diagnosing VDO Collapse: Patients with suspected loss of vertical dimension of occlusion, where the true VDO must be objectively determined before treatment planning.
- Testing Orthopedic Stability in Complex Cases: Patients with complex occlusal, TMD, or prosthetic presentations where the orthopedic joint relationship must be verified before committing to definitive treatment.
- Pre-Treatment Diagnostic Phase: As a diagnostic reference appliance in the planning phase of comprehensive restorative, implant, or orthodontic-orthognathic cases.
B Splint Feasibility Checklist:
[✓] Adequate remaining dentition for stable bilateral seating
[✓] Controlled periodontal status with no active inflammation
[✓] Sufficient interocclusal space for dual-arch components
[✓] Patient compliance for wear during diagnostic phase
[✗] Insufficient dentition for stable bilateral seating (Contraindicated)
Case Selection Criteria
- Adequate Remaining Dentition: Both arches must have sufficient remaining teeth to support stable seating of the maxillary and mandibular components. Mobile teeth, fractured crowns, or missing units compromise seating stability and should be addressed before delivery.
- Controlled Periodontal Status: Active periodontitis, acute peri-implant inflammation, or significant tooth mobility must be controlled before B Splint wear.
- Sufficient Interocclusal Space: The dual-arch components must fit within the patient’s available interocclusal space without inducing discomfort or premature contact. Patients with severely restricted vertical opening may not tolerate the appliance.
- Patient Compliance During Diagnostic Phase: The B Splint is designed for controlled wear during the diagnostic phase. Patients must understand and commit to the wear protocol and the required follow-up appointments.
The Role of Bimanual Joint Manipulation in Diagnosis
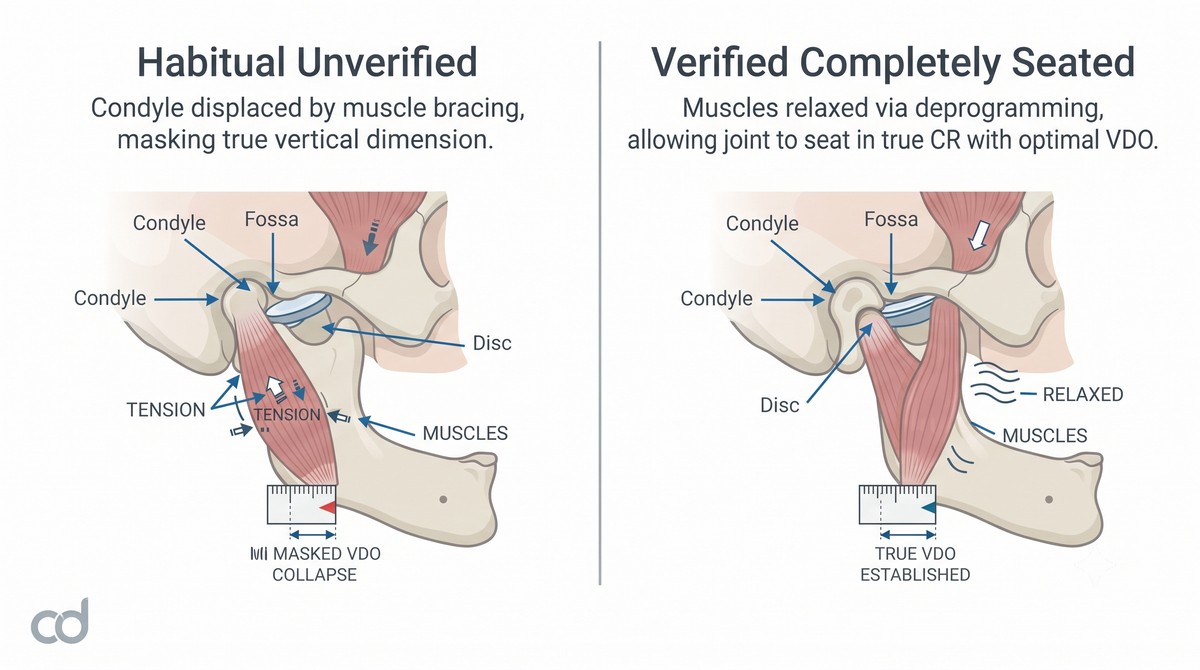
Bimanual joint manipulation is the gold-standard clinical technique for verifying true condylar seating. The clinician places the thumbs on the mandibular symphysis, the fingers behind the mandibular angles, and gently manipulates the mandible into its anterior-superior condylar position. Without a diagnostic appliance in place, this technique is often confounded by muscle bracing, habitual engram interference, or posterior tooth contact that prevents complete seating.
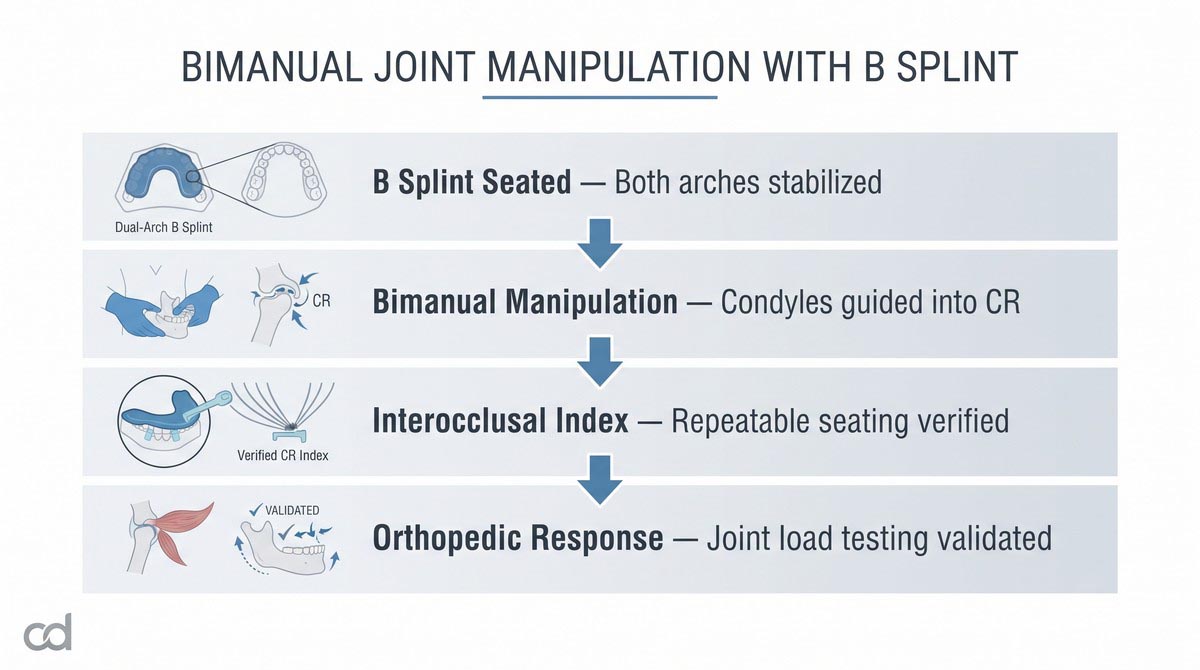
With the B Splint seated, bimanual manipulation becomes significantly more reliable. The dual-arch interlock provides a stable reference platform, and the interocclusal index points register the mandibular position as the condyles seat. This integration of bimanual technique with the B Splint is essential for accurate diagnosis of joint seating and VDO.
VDO Collapse Diagnostic and Its Clinical Value
The VDO collapse diagnostic is one of the most important applications of the B Splint. Patients with undiagnosed VDO loss often present with:
- Compensated tooth wear that masks the true vertical dimension
- Reduced lower facial height and an aging facial profile
- Progressive overclosure with associated TMJ symptoms
- Restorative failures related to insufficient interocclusal space
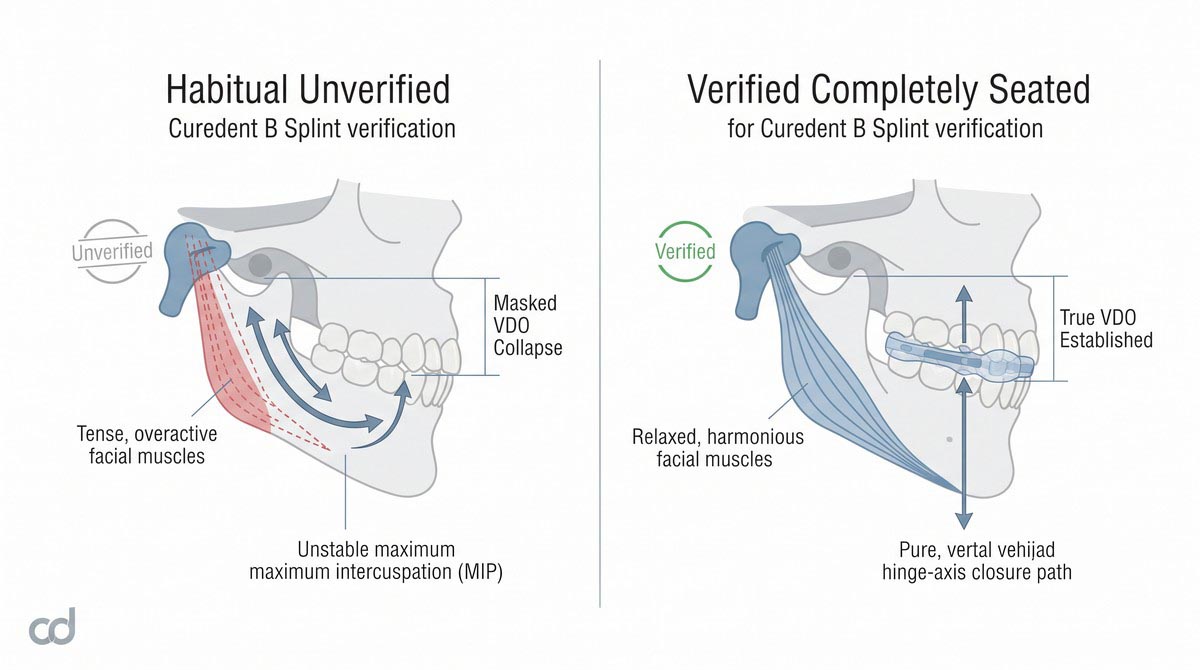
By seating the B Splint at the planned VDO and performing bimanual manipulation with the appliance in place, the clinician can objectively determine whether the patient’s true VDO is greater than the current habitual position. If the patient seats comfortably at the planned VDO with the B Splint in place, this confirms VDO collapse and supports a reconstruction plan that restores the lost vertical dimension.
Typical Clinical Scenarios
- Full-Mouth Rehabilitation Planning: Patients scheduled for comprehensive occlusal reconstruction where verified condylar seating and objective VDO determination are essential prerequisites.
- Implant-Supported Full-Arch Cases: Patients requiring multi-unit implant restorations where inaccurate VDO or unverified condylar position could compromise passive fit and long-term success.
- Complex TMD with Suspected VDO Collapse: Patients presenting with TMD symptoms and signs of vertical dimension loss where objective diagnostic testing is required before definitive therapy.
- Orthodontic-Orthognathic Surgical Planning: Patients requiring combined orthodontic and surgical treatment where accurate condylar seating and VDO determination are critical to surgical planning.
Section 4: Clinical Workflow & Diagnostic Protocol

Step 1: Data Acquisition
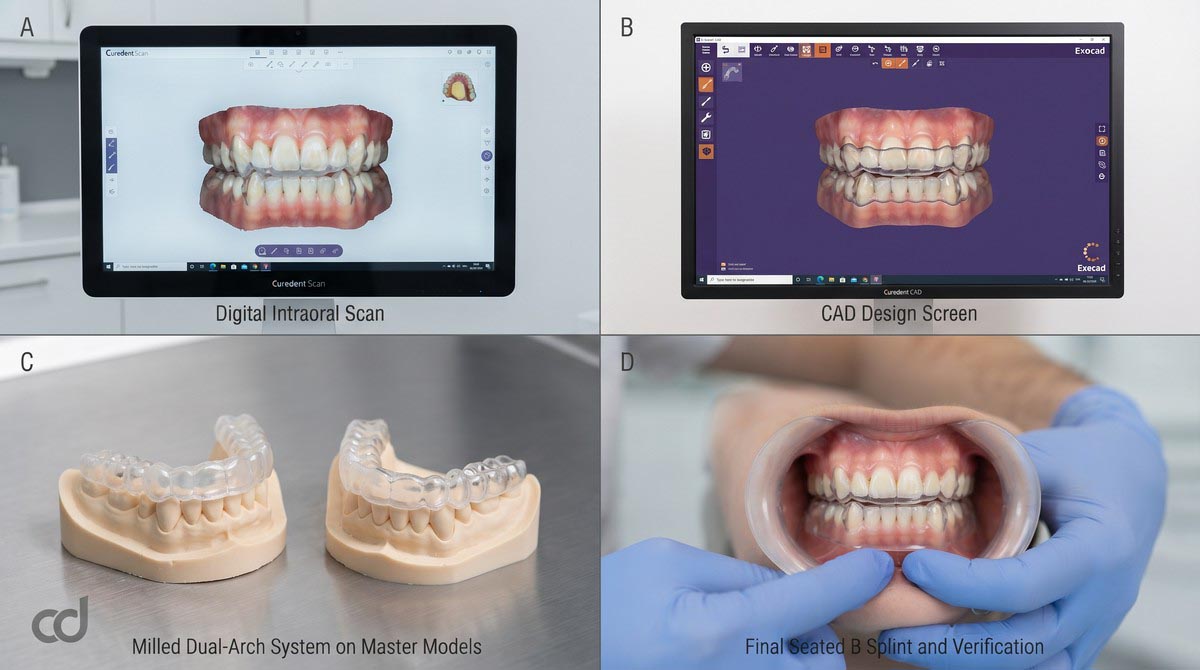
Acquire a high-resolution optical intraoral scan of the maxillary and mandibular arches with accurate soft-tissue margin capture. Record the patient’s occlusal registration and, when indicated, submit mounted articulator models or facebow transfer data to support accurate dual-arch design. Document the patient’s current opening range, VDO appearance, and any TMD symptoms.
Step 2: Digital CAD Design
Curedent digital engineers design both components within a virtual articulator environment. The maxillary and mandibular components are designed to interlock through precision-milled index points, with posterior contact zones providing stable vertical stops. The clinician reviews and approves the virtual design before milling.
Step 3: 5-Axis Milling and Finishing
The approved design is milled from two medical-grade PMMA blanks on a 5-axis milling unit, producing both components as monolithic structures with precise interocclusal index points and clean marginal contours. Both components are hand-polished and inspected for surface uniformity before dispatch.
Step 4: Delivery Verification
Upon receiving the appliance, inspect both components on the master models: confirm complete seating on both arches, verify that the interocclusal index points engage precisely, check the posterior contact zones for stable vertical stops, and ensure margins are smooth and rounded.
Step 5: Chairside Seating and Bimanual Manipulation Verification
- Seat the maxillary component on the maxillary arch using gentle finger pressure across the posterior segments.
- Seat the mandibular component on the mandibular arch using the same technique.
- Verify passive seating on both arches: each component should seat without rocking and remain stable when the patient opens and closes.
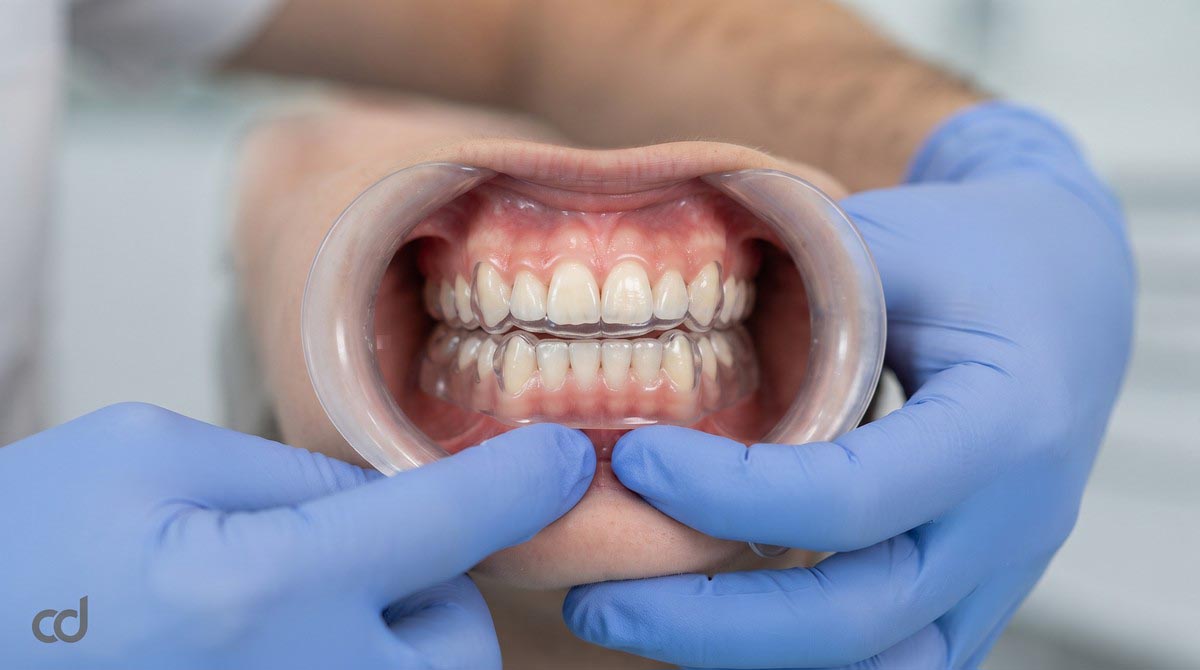
- Verify completely seated condylar position: place the thumbs on the mandibular symphysis and the fingers behind the mandibular angles. Gently guide the mandible into its anterior-superior condylar position while the B Splint is seated. The condyles should seat smoothly into the glenoid fossae without deflection.
- Confirm that the interocclusal index points engage precisely as the condyles seat: the maxillary and mandibular components should interlock in a repeatable, verifiable position.
- Assess the patient’s orthopedic response: the joint should seat without pain, muscle guarding, or deflection.

Step 6: Joint Load Testing and Interocclusal Clearance Validation
With the B Splint seated and the condyles verified in CR, perform controlled joint load testing. Apply gentle posterior and superior pressure to the mandible and observe the patient’s orthopedic response. A stable, non-painful response confirms orthopedic stability and validates the planned treatment position. Then perform interocclusal clearance verification: confirm that the posterior contact zones provide stable vertical stops at the planned VDO, with no premature contact, no overclosure, and no interocclusal interference.
Step 7: Diagnostic Record Capture and Treatment Planning
With the B Splint seated and the condyles verified in CR, capture diagnostic records:
- Centric relation bite registration using rigid bite registration material or digital jaw tracking.
- Photographic documentation of the seated appliance and the patient’s facial profile.
- Articulator mounting or digital transfer of the CR position for prosthetic design.
- VDO determination based on the verified seating position.
Transfer these records to the definitive treatment planning workflow for prosthetic design, orthodontic treatment, or combined rehabilitation.
Verification Sequence and Hygiene Considerations
The verification sequence must be performed in a specific order to ensure diagnostic accuracy: seat both components, verify passive seating, perform bimanual manipulation, confirm interocclusal index engagement, perform joint load testing, then capture diagnostic records. Skipping or reordering steps compromises the reliability of the diagnostic output. Strict hygiene is essential during B Splint wear: the appliance should be stored dry in a ventilated case when not in the mouth. Patients should be advised against using boiling water, alcohol-based mouthwash, or abrasive denture cleaners, all of which can degrade the PMMA surface and compromise the precision interocclusal index points.
Section 5: Technical Specifications & Diagnostic Standards
Certified Technical Specifications
The Curedent B Splint is manufactured to strict biomedical and dimensional tolerances to ensure reliable diagnostic output and repeatable interocclusal seating.
| Parameter | Specification | Clinical Relevance |
|---|---|---|
| Material | Medical-grade milled PMMA (or Class IIa biocompatible resin) | High rigidity, zero polymerization shrinkage |
| Fabrication method | Precision 3D printing or 5-axis milling | Uniform surface flatness, precise index geometry |
| Design | Dual-arch diagnostic system (maxillary + mandibular) | Stable bilateral support during bimanual manipulation |
| Interocclusal fit tolerance | Engineered for precise arch interlock (< 0.05 mm) | Repeatable seating and reproducible records |
| Index point accuracy | Case-dependent, milled precision | Reliable interocclusal registration |
| Surface finish | Polished, uniform | Prevents wear facets and contact instability |
| Fit tolerance | Engineered for stable seating on both arches | Passive seating without rocking |
| Diagnostic purpose | Verify completely seated condylar position | Objective CR and VDO determination |
| Retention type | Removable dual-arch diagnostic appliance | Stable during diagnostic wear sessions |
| Sterilization | Delivered ready for clinical use | Cleaned and packaged for immediate operatory use |
Interocclusal Precision and Diagnostic Reliability
The diagnostic accuracy of the B Splint depends on precise milling tolerances:
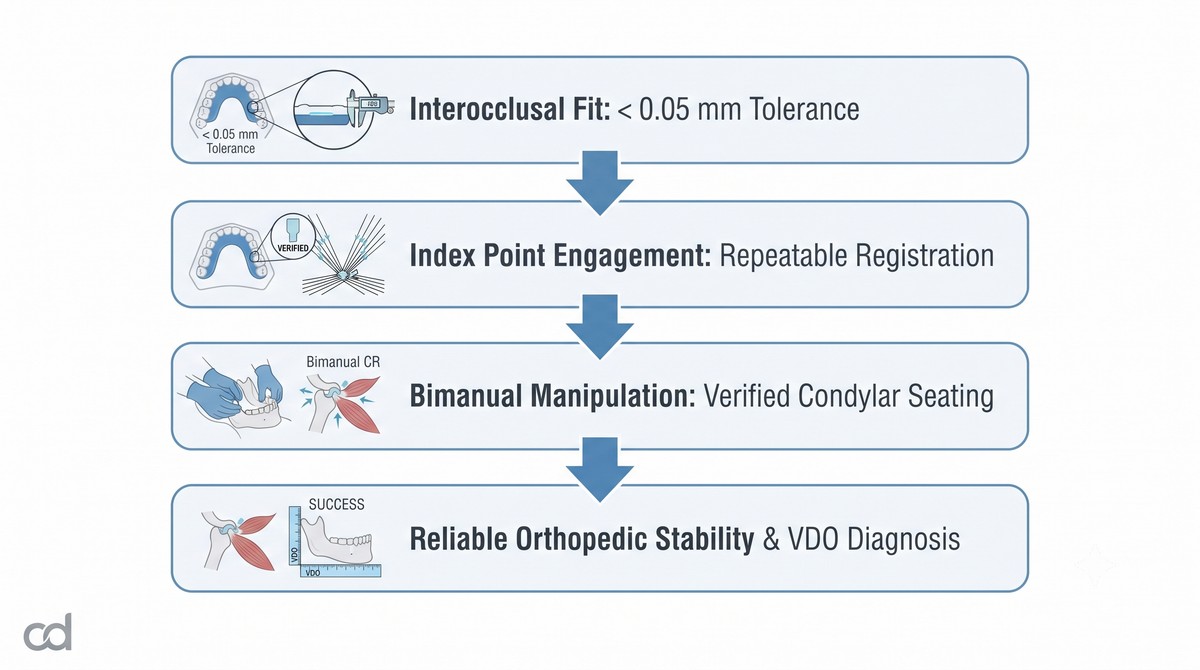
- Interocclusal Fit Tolerance: The interlock between the maxillary and mandibular components is milled to a tolerance below 0.05 mm, ensuring that diagnostic records captured with the appliance in place are reproducible across multiple appointments.
- Index Point Accuracy: The interocclusal index points are milled to case-dependent precision, ensuring reliable registration of the mandibular position as the condyles seat.
- Arch Adaptation: Both components are engineered to seat passively across their respective arches, with fit tolerances below 0.05 mm to prevent deflection or displacement during diagnostic testing.
Orthopedic Stability Verification and Its Clinical Value
The ultimate purpose of the B Splint is to verify orthopedic stability—the condition in which the condyles are seated in their true musculoskeletal position without pain, deflection, or muscle guarding. When the B Splint is seated and bimanual manipulation confirms complete condylar seating, the clinician has objective evidence that the planned treatment position is orthopedically stable. This verification is essential for:
- Full-mouth rehabilitation planning where prosthetic design depends on verified CR
- Implant-supported reconstruction where framework passivity depends on accurate VDO
- Orthodontic-orthognathic surgical planning where skeletal position depends on verified joint seating
- Complex TMD diagnosis where joint position determines the treatment pathway
Section 6: Clinical Benefits & Practice Impact

Patient-Level Clinical Benefits
- Reliable Diagnostic Seating: The dual-arch interlock and bimanual manipulation capability provide a stable, verifiable reference for true condylar seating—eliminating the diagnostic uncertainty that plagues habitual bite records.
- Accurate VDO Assessment: The B Splint provides an objective platform for VDO collapse diagnostic, allowing the clinician to determine the patient’s true vertical dimension before committing to definitive treatment.
- Informed Treatment Planning: With verified CR and VDO, the clinician can plan restorative, implant, or surgical treatment with confidence, reducing the risk of mid-treatment complications or prosthetic failure.
- Reduced Risk of Misdiagnosis: By eliminating muscle bracing and habitual engram interference from the diagnostic process, the B Splint improves diagnostic accuracy and reduces the likelihood of treatment based on unreliable records.
Practice-Level Operational Advantages
- Routine Adoption of Diagnostic Joint Protocols: Integrating the B Splint into the diagnostic workflow standardizes condylar seating verification and VDO assessment across complex cases.
- Reduced Chairside Guesswork: With verified CR and VDO records, prosthetic design, occlusal adjustments, and rehabilitation planning become predictable processes rather than exercises in clinical intuition.
- Improved Predictability in Complex Rehabilitation Cases: Accurate CR transfer to the articulator or digital design environment reduces the risk of occlusal discrepancies, fractured provisionals, and unplanned vertical dimension corrections.
- Standardization Across Complex Cases: A structured diagnostic protocol allows clinical teams to manage complex rehabilitation cases with consistent, repeatable workflows.
Dual-Arch Diagnostics as a Modern Standard
Single-arch diagnostic splints have long been the standard in occlusal therapy, but they provide only one reference plane. The dual-arch B Splint provides two simultaneous references, enabling the clinician to verify joint seating and VDO in a single diagnostic procedure. This dual-arch approach is increasingly recognized as a modern standard in complex rehabilitation planning. The Curedent B Splint modernizes the classic Dawson design with precision-milled construction, engineered interocclusal index geometry, and a structured diagnostic protocol. By verifying true condylar seating and VDO before committing to definitive therapy, clinicians can plan and execute complex rehabilitation cases with confidence.
Integrating the B Splint with Other Curedent Appliances
The B Splint is often used as a diagnostic reference in the pre-treatment phase of complex restorative workflows. For patients requiring acute muscle decompression before diagnostic testing, the Curedent Anterior Bite Splint provides rapid neuromuscular relaxation. For single-point deprogramming before CR recording, the Curedent Kois Deprogrammer offers precise engram disruption. After diagnostic verification, patients typically transition to a Curedent Occlusal Splint for long-term stabilization during the rehabilitation phase.
Section 7: Ordering, FAQ & Call to Action
Simple Three-Step Ordering Workflow
Ordering the Curedent B Splint through the doctor portal is designed to be efficient:
[Step 1: Upload Records] ──► [Step 2: Review Digital Design] ──► [Step 3: Receive B Splint]
Scan + Occlusal Data CAD Approval via Portal Milled & Polished
- Upload Case Records: Access the Curedent portal and upload the patient’s optical intraoral scans (maxillary, mandibular, and bite registration in STL or PLY format) along with any mounted articulator model data or facebow records.
- Review Digital Design: Curedent engineers design both components within a virtual articulator, establish the interocclusal index points, position the posterior contact zones, and verify interocclusal clearance. Review and approve the design via the interactive web viewer.
- Receive and Deliver: Curedent mills both components from medical-grade PMMA, hand-polishes all surfaces, verifies interocclusal index engagement and margin adaptation, packages the dual-arch system in protective clinical casing, and dispatches it directly to your practice.
Standard Shipment Package Contents:

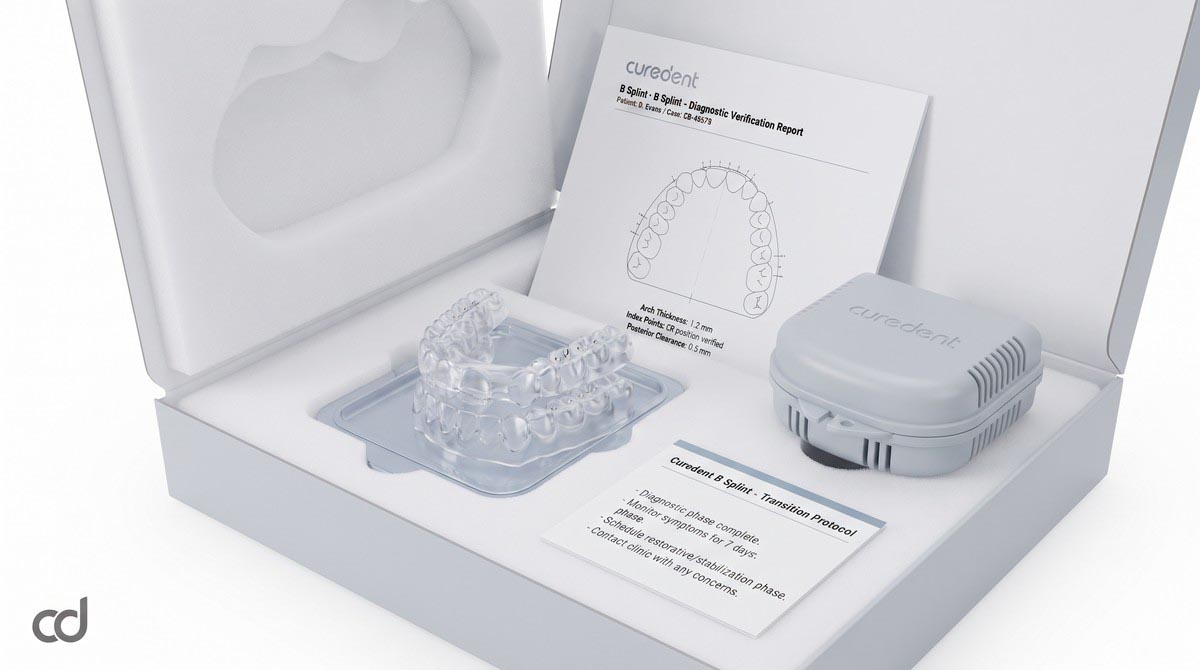
Frequently Asked Questions
Do I need mounted models to order a Curedent B Splint?
Mounted models or facebow transfer data are recommended but not mandatory. For straightforward diagnostic cases, digital occlusal registration and intraoral scans are sufficient. For complex full-mouth rehabilitation planning or cases with significant VDO uncertainty, submitting mounted articulator models improves the accuracy of the interocclusal index design.
How long should the patient wear the B Splint?
The B Splint is designed for diagnostic-phase wear, typically minutes to a few hours per session during the diagnostic appointments. It is not designed for overnight or long-term wear. Once diagnostic records are captured and the treatment plan is finalized, transition the patient to a long-term stabilization appliance.
Can the B Splint be used for long-term therapy?
No. The B Splint is a diagnostic appliance designed to verify condylar seating and VDO before definitive treatment. Long-term stabilization should be managed with a full-coverage appliance such as the Curedent Occlusal Splint. Prolonged B Splint wear is not recommended and may not provide the continuous protective coverage needed for long-term therapy.
How is the B Splint different from a Michigan splint?
A Michigan splint (full-coverage occlusal splint) is a single-arch, long-term stabilization appliance. The B Splint is a dual-arch diagnostic system designed to verify condylar seating and VDO before definitive treatment. The two appliances serve different clinical purposes: the Michigan splint for long-term stabilization, the B Splint for diagnostic verification.
Can I adjust the B Splint chairside?
Yes. The milled PMMA surfaces can be refined chairside using fine finishing burs to adjust isolated heavy contacts or to fine-tune the interocclusal index points. However, because both components are precision-milled, only minor adjustments should be needed after proper digital design. Any adjustment should be documented in the case record.
Suggested Clinical Solutions
- Transition to long-term stabilization with the Curedent Occlusal Splint.
- Manage acute TMD muscle spasm with the Curedent Anterior Bite Splint.
- Enable precise CR recording with the Curedent Kois Deprogrammer.